Saturday, 30 May 2026

What to Expect at Your First Chiropractic Appointment in Sydney

First chiropractic appointments in Sydney generate a consistent set of questions before patients even walk through the door. Will it hurt? Will the neck be cracked? How long will it take? What information is needed?

 At Spine and Posture Care, these are the questions the clinical team hears most often from people booking their first visit with a chiropractor in Sydney CBD. The short answer is that a first appointment is not a treatment session. It is a structured assessment. Understanding what actually happens, and in what order, removes most of the uncertainty before arriving.

How the First Appointment Differs from a Regular Visit

A first chiropractic appointment is longer, more detailed, and structured differently from every subsequent visit. Regular appointments at an established chiropractic practice typically run 15 to 30 minutes and focus on treatment. A first appointment runs 45 to 60 minutes and focuses primarily on assessment, history, and diagnosis.

The reason is straightforward. A chiropractor cannot treat a condition that has not been properly assessed. Before any hands-on treatment begins, the clinical picture needs to be complete. That means understanding the patient’s history, the nature of the complaint, any previous injuries or conditions, and the results of a physical examination. The full range of conditions we treat at both Sydney CBD locations spans back pain, neck pain, headaches, sciatica, posture problems, and bulging discs. Each requires a different assessment pathway.

Patients who attend a first appointment expecting to receive the same experience as a regular adjustment are sometimes surprised by the amount of time spent on questions and assessment before any treatment begins. This is by design, not by accident.

What Happens Step by Step

The first appointment at a Sydney chiropractic clinic follows a consistent structure. The sequence below is how it unfolds at Spine and Posture Care, at both the Macquarie Street and Barangaroo chiropractic clinic locations.

Step 1: Intake Form Completion (Before or on Arrival)

New patients complete an intake form before or at the start of the appointment. This covers the chief complaint, symptom duration, location and behaviour of the pain, relevant medical history, medications, previous imaging or scans, and current lifestyle factors including work posture and activity level. The more detail provided on this form, the more efficiently the consultation can proceed.

Patients who have recent scan results, such as an MRI or X-ray report, should bring a copy. This prevents duplication of imaging and gives the chiropractor a documented baseline to work from.

Step 2: The Consultation (10 to 15 Minutes)

The chiropractor reviews the intake form and conducts a structured verbal consultation. The focus is on understanding the full picture of the complaint. This covers when it started, what makes it better or worse, whether pain radiates, how it affects daily activities, and what has already been tried. Previous treatment outcomes are also relevant.

This is not a rushed intake. The information gathered here directly shapes which orthopaedic and neurological tests are performed in the assessment phase. A thorough consultation leads to a more targeted examination.

Step 3: The Physical Assessment (15 to 20 Minutes)

The physical assessment is the clinical core of the first appointment. It typically includes the following components.

Postural assessment. The patient is observed standing from the front, back, and side. The chiropractor notes any lateral deviation of the spine, head position, shoulder level, pelvic symmetry, and overall spinal curvature. This provides a visual baseline that is used to track progress throughout care.

Range of motion testing. Active and passive movement is assessed across the relevant spinal regions. The chiropractor notes which movements are restricted, which reproduce symptoms, and where the limitation originates.

Orthopaedic testing. A series of specific clinical tests is used to identify the likely structure involved. These tests help differentiate between disc involvement, joint restriction, nerve irritation, and muscular causes of the presenting complaint.

Neurological screening. For presentations involving radiating pain, numbness, or tingling, reflex testing and sensory screening help identify whether nerve function is affected and at which level.

Motion palpation. The chiropractor manually assesses each vertebral segment for mobility, tenderness, and joint restriction. This is the most direct assessment of spinal joint function and is the foundation for determining which segments require treatment.

Step 4: Findings and Care Plan Discussion (10 Minutes)

After the assessment, the chiropractor explains the findings in plain language. This includes identifying the structures involved, the likely cause of the symptoms, and what the treatment pathway looks like. A care plan is proposed. It typically covers an initial phase of sessions, a reassessment milestone, and a transition to either maintenance or discharge.

This is also the point at which the patient can ask questions about the diagnosis, the proposed treatment approach, or anything covered during the assessment. No treatment begins until the patient understands and agrees to proceed.

Step 5: First Treatment (10 to 15 Minutes, Where Appropriate)

In most cases, gentle treatment begins on the same day as the first assessment. This is not the same depth of treatment as a regular session, and the priority is to introduce the patient to the techniques involved rather than to deliver the full treatment protocol. For presentations involving significant acute pain or where further imaging is required before treatment, the first session may be assessment only.

What Each Chiropractic Technique Feels Like

One of the most common concerns before a first appointment is uncertainty about what the treatment will feel like physically. Different techniques produce different sensations. Understanding what to expect removes most of the anxiety.

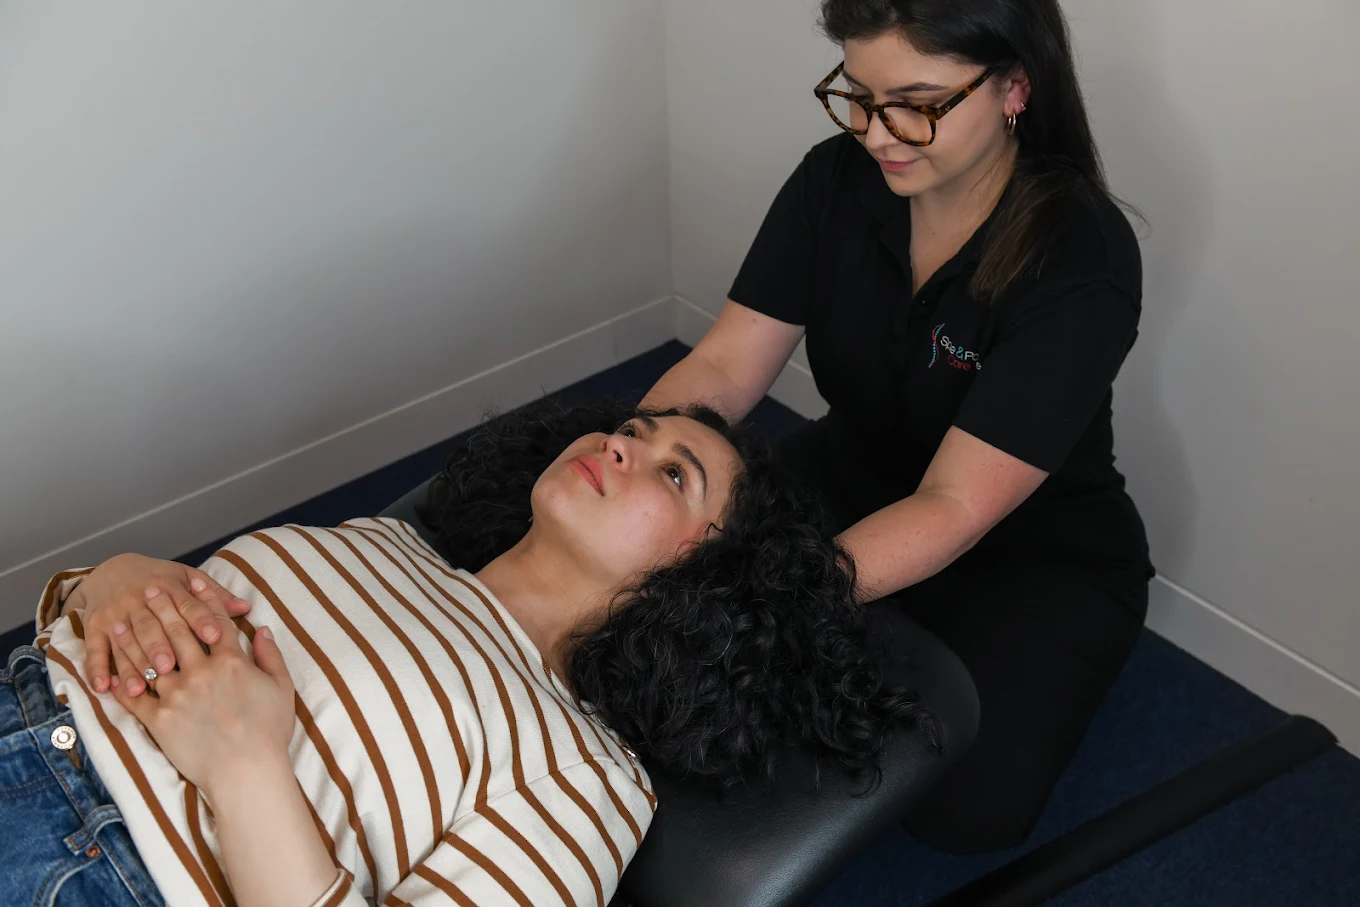
Diversified adjustment. This is the most recognisable chiropractic technique. The chiropractor applies a controlled, specific thrust to a restricted spinal joint. The thrust is fast and precise. An audible pop or click is common. This sound is caused by gas released within the joint capsule. It is not the sound of bones cracking. The thrust itself is momentary. Patients typically describe it as pressure followed by an immediate sense of release or lightened tension in the area.

Drop piece technique. A specialised table with drop-release sections assists the adjustment. The section drops slightly as the thrust is applied, reducing the force required. This produces a firm but gentler sensation than the diversified technique. It is commonly used for lumbar and pelvic adjustments.

Activator method. A small spring-loaded instrument applies a precise, low-force impulse to a specific joint. There is no rotation or thrust involved. The sensation is a light tap. This technique is suitable for patients who are anxious about manual adjustment, are managing osteoporosis, or have had recent surgery.

Joint mobilisation. The joint is moved gently and repeatedly through its available range without a thrust. This technique feels like a rhythmic passive stretch. It is commonly used for stiff thoracic segments or for gentle introduction to care.

Comparison between chiropractor and physiotherapist by Spine and Posture Care for treatment needs

Common Concerns Before a First Appointment

Will the neck be manipulated? Cervical adjustment is only performed when the assessment indicates it is clinically appropriate. Patients who prefer not to have cervical adjustment can request alternative techniques at any point. Neck mobilisation, soft tissue work, and upper thoracic adjustment can address many neck complaints without cervical manipulation.

Is chiropractic safe? Chiropractors in Australia are registered health professionals regulated by AHPRA. At Spine and Posture Care, every practitioner holds current registration and all treatment decisions follow evidence-based clinical guidelines. Safety screening is part of the assessment process before any treatment begins.

What if treatment makes things worse? Post-treatment soreness in the 12 to 24 hours following an adjustment is common, particularly after the first few sessions. This is a normal inflammatory response and typically resolves within a day. It is different from the original complaint and should not be confused with the condition worsening.

Booking a first appointment at a Sydney CBD clinic should be straightforward. Call (02) 8040 9922 or get in touch here and a member of the team will confirm availability and answer any questions before the visit.

What Happens After the First Visit

The period immediately following the first appointment is when most new patients decide whether to proceed with care. The chiropractor will have outlined a recommended treatment plan during the findings discussion. That plan typically consists of an initial phase of more frequent visits, followed by a reassessment and a transition to a maintenance schedule.

Patients are not obligated to commit to the full plan at the first appointment. The recommendation is presented and discussed, but the decision to proceed at any pace is made by the patient. A reputable clinic will not pressure patients into a long-term commitment before they have had a chance to assess whether the first session was useful.

Home care recommendations are part of the first appointment at most Sydney CBD chiropractic clinics. These may include advice on sleep position, brief daily exercises, posture modifications, or ice and heat application. These recommendations bridge the gap between clinic sessions and significantly influence how quickly the condition responds.

How to Prepare for Best Results

Wear comfortable clothing. Clothing that allows the chiropractor to assess the spine and perform orthopaedic tests without restriction is ideal. Activewear or loose-fitting clothing is appropriate. For CBD workers attending during a lunch break, a change of shirt is helpful but not essential.

Bring relevant documentation. Any existing MRI reports, X-rays, or specialist letters should be brought to the first appointment. If these are saved electronically, having them accessible on a phone or sent ahead is equally useful.

Arrive five minutes early. The intake form needs to be completed before the consultation begins. Arriving on time but needing to fill in the form first cuts into the consultation time, not the assessment time.

Plan for 60 minutes. The first appointment at most Sydney CBD clinics runs close to an hour. Scheduling it with a clear hour on either side avoids the situation of being rushed through the findings discussion.

Note symptom patterns. Being able to describe when the pain is worst, what activities aggravate it, and whether it changes through the day gives the chiropractor more precise information in less time. A brief mental note or written list before arriving is worth preparing.

First Appointment at a Glance

Stage Duration What Happens
Intake form 5 to 10 min Health history, symptom detail, consent
Consultation 10 to 15 min Verbal assessment of complaint, history
Physical assessment 15 to 20 min Posture, range of motion, orthopaedic and neuro tests, palpation
Findings discussion 10 min Diagnosis explained, care plan proposed
First treatment 10 to 15 min Initial gentle treatment if appropriate
Total 45 to 60 min

When to Book a First Chiropractic Appointment in Sydney

A first appointment is appropriate when a musculoskeletal complaint has been present for more than a few days, is limiting daily activity, or is not resolving on its own. Back pain, neck pain, headaches with a spinal or postural origin, sciatica, and poor posture are among the most common reasons patients book. None of these require a GP referral for a private chiropractic visit.

All chiropractors in Australia are regulated by AHPRA, the Australian Health Practitioner Regulation Agency. Practitioner registration can be verified directly on the AHPRA website before booking. This is worth doing for anyone who has not previously seen a chiropractor and wants to confirm the practitioner’s standing.

Sydney CBD chiropractic clinics that offer early morning, lunchtime, and late afternoon appointments are accessible for full-time workers without requiring time off. This is worth confirming at the time of booking, particularly for new patients who need a longer initial appointment slot.

Conclusion

A first chiropractic appointment is a structured clinical assessment that ends with a diagnosis, a treatment recommendation, and typically a first session of gentle care. The process is methodical, not unpredictable. Knowing what to bring, how long to allow, and what questions to ask beforehand makes the experience productive from the first visit.

For patients comparing options before booking, the guide to choosing a chiropractor vs physiotherapist in Sydney covers the differences in approach and how to identify which pathway suits a specific complaint. Spine and Posture Care offers first appointments at both the Macquarie Street and Barangaroo CBD locations throughout the week, including early morning and Saturday slots.

To book a first appointment or ask any questions before attending, call Spine and Posture Care on (02) 8040 9922 or Contact the clinic directly. No referral is required.

Frequently Asked Questions

How long does the first chiropractic appointment take in Sydney?

A first chiropractic appointment at a Sydney CBD clinic typically runs 45 to 60 minutes. This is significantly longer than a regular appointment because the first visit is primarily an assessment rather than a treatment session. The time spans five stages: an intake form, a verbal consultation, a physical assessment, a findings discussion, and where appropriate, a first gentle treatment. Each stage has a clear clinical purpose. Patients should plan for a full hour and avoid scheduling back-to-back commitments immediately after.

Do chiropractors always crack the back at the first appointment?

No. The adjustment technique used depends on the assessment findings and the patient’s preference. Not all chiropractic treatment involves audible joint sounds. Techniques such as activator instrument adjusting, joint mobilisation, and drop piece technique are effective alternatives that do not produce the characteristic pop. Patients who are uncomfortable with manual adjustment or have concerns about any technique should communicate this before treatment begins. A registered chiropractor will always have alternative approaches available.

Do I need a referral to see a chiropractor in Sydney?

No referral is required to book a first chiropractic appointment in Sydney. Any patient can book directly as a private patient and pay the consultation fee at the time of the visit. A GP referral is only needed if the patient intends to claim a Medicare rebate through the GPCCMP pathway for a qualifying chronic condition. For most new patients attending for the first time, a referral is not necessary and the appointment can be booked online or by phone.

What should I wear to my first chiropractic appointment?

Comfortable clothing that allows free movement is the most practical choice. Activewear or clothing that can be easily adjusted is ideal because the chiropractor needs to assess posture, perform range of motion testing, and conduct palpation of the spine. For CBD office workers attending during a lunch break, changing out of work clothes entirely is not essential. Loose-fitting options are more practical than a fitted suit, but either works.

Will I receive treatment at my first chiropractic appointment?

In most cases, gentle treatment is provided at the first appointment after the assessment and findings discussion are complete. The depth of treatment is lighter than a regular session. The focus is on introducing the patient to the techniques involved and addressing the most restricted or symptomatic areas. In cases where the presentation requires imaging before treatment, or where the patient prefers to consider the care plan before proceeding, the first session may be assessment only. No treatment is ever provided without the patient’s understanding and agreement.

The post What to Expect at Your First Chiropractic Appointment in Sydney appeared first on Spine and Posture Care.


from Spine and Posture Care https://ift.tt/507HKvJ
via IFTTT

Friday, 29 May 2026

Does Medicare Cover Chiropractic in Australia? A 2026 Guide for Sydney Patients

One of the most common questions at the front desk of any chiropractic clinic in Sydney is some version of: does Medicare cover this? The question usually comes up right after the first appointment, when a patient is deciding whether to continue with care and wondering what the ongoing cost will look like. 

Spine and Posture Care hears it at both its Sydney CBD locations, and the answer involves more than a simple yes or no. Chiropractic care in Sydney CBD is accessible through several payment pathways, and understanding each one helps patients make informed decisions before they commit to a treatment plan.

The Short Answer for Sydney Patients

Medicare does not automatically cover standard chiropractic visits. Patients cannot walk in, present a Medicare card, and receive a rebate for a routine adjustment. That is not how Medicare works for allied health services.

However, there is a specific pathway that does allow Medicare rebates for chiropractic. Patients with a chronic back pain treatment or other chronic musculoskeletal condition may be eligible for up to five subsidised allied health sessions per calendar year. These sessions are funded through a GP Chronic Condition Management Plan. This is commonly called a GPCCMP, or by its older names: CDM plan, EPC plan, or GP Management Plan.

Outside this pathway, chiropractic is treated as a private health service. The full consultation fee applies, with no Medicare contribution. Private health extras cover is the main alternative for reducing out-of-pocket costs in that case.

What Is the GPCCMP and How Does It Work in 2026?

The GPCCMP is the current Medicare framework for coordinating care for patients with chronic conditions. It replaced the older GP Management Plan (GPMP), Team Care Arrangement (TCA), and Enhanced Primary Care (EPC) plan structures as of 1 July 2025. The change simplified the system into a single plan type, but the core entitlement remains the same: up to five allied health sessions per calendar year with a Medicare rebate.

Chiropractic is a listed eligible service under the GPCCMP. Spine and Posture Care is a registered allied health provider, and patients can ask their GP to refer them to a back pain chiropractor in Sydney directly when the plan is prepared.

What Qualifies as a Chronic Condition?

A chronic condition is defined as one that has lasted, or is expected to last, at least six months. Common qualifying conditions include chronic lower back pain, neck pain, osteoarthritis, scoliosis, and other ongoing musculoskeletal problems. The GP makes the final clinical determination. Not all back pain qualifies. A recent acute injury or a short-term sprain is unlikely to meet the threshold, but a condition that has been present for six months or more typically does.

The Step-by-Step Process

Step 1: Book an appointment with a GP. The patient discusses the chronic condition and whether a GPCCMP is appropriate. MyMedicare-registered patients must access the plan through their registered practice.

Step 2: The GP prepares the plan. The GP documents the condition, treatment goals, and which allied health services are appropriate. Chiropractic is specified in the plan if that is the intended referral.

Step 3: A referral letter is issued. The referral is addressed to the chiropractic provider. It is valid for 18 months from the first service date if no timeframe is stated.

Step 4: Book chiropractic appointments. The patient brings the referral to the clinic. The chiropractor processes the Medicare rebate at the time of the visit, typically through HICAPS or online claiming.

Step 5: Track the five sessions. The five sessions are shared across all allied health services on the plan. A patient seeing both a chiropractor and a physiotherapist under the same plan uses sessions from the same five-session pool.

Important 2026 note: Patients who had an older GPMP or TCA in place before 1 July 2025 can continue accessing services under those plans until 30 June 2027. No immediate action is required, but new plans from mid-2025 onwards are issued as GPCCMPs.

Comparison between chiropractor and physiotherapist by Spine and Posture Care for treatment needs

What the Medicare Rebate Actually Covers

The Medicare rebate for chiropractic under the GPCCMP is approximately $56 to $62 per session as of 2026, following the July 2025 MBS indexation. This figure is reviewed annually, so patients should confirm the current rebate amount with their clinic or Services Australia before planning their care budget.

Most chiropractic clinics in Sydney CBD charge between $80 and $120 for a standard consultation. That creates a gap payment of between $20 and $60 per session, depending on the clinic’s fee structure. Some providers choose to bulk bill GPCCMP patients, meaning they accept the Medicare rebate as full payment with no out-of-pocket cost. This is less common in inner-city Sydney where clinic overheads are higher.

The five sessions are a calendar-year entitlement, running from 1 January to 31 December. Sessions do not roll over. Any unused sessions at year end are forfeited.

Payment Type What It Covers Gap Payment
GPCCMP (Medicare) ~$56-62 per session, up to 5 per year Clinic fee minus rebate
Bulk billing (some providers) Full session cost covered by Medicare $0
Private health extras Varies by fund and policy tier Clinic fee minus fund rebate
Full private fee No rebate Full clinic fee

Private Health Insurance for Chiropractic in Sydney

Private health extras cover is the main way patients without a GPCCMP offset chiropractic costs. It also supplements Medicare sessions for patients who need more than five visits per year. At Spine and Posture Care, patients with extras cover can process their claim in clinic through HICAPS at the time of the appointment.

Most mid-range extras policies cover between $300 and $600 per year for chiropractic, with per-visit limits that typically range from $30 to $55. Higher-tier policies may offer up to $800 or more annually. The per-visit cap is usually the binding constraint rather than the annual limit for patients who attend regularly.

Watch for combined limits. Many policies pool chiropractic with physiotherapy, osteopathy, and remedial massage under a single musculoskeletal or body therapies category. Claiming across multiple therapies from the same pool depletes the annual limit faster.

Waiting periods. Most funds apply a standard two-month waiting period on extras cover before chiropractic claims can be made. New members joining specifically for chiropractic cover should factor this in.

Annual limit reset dates. Most funds reset annual limits on 1 January or 1 April. Patients who join close to a reset date may have limited time to claim before the limit refreshes.

Unsure which payment pathway applies? Call (02) 8040 9922 or get in touch here and the team at our Sydney CBD clinic can clarify costs and help with the booking process.

Other Payment Pathways: DVA, WorkCover, and CTP

DVA Gold Card holders receive chiropractic care covered at no cost, provided the treating chiropractor is a registered DVA provider and the treatment is for an accepted condition or general health care. DVA White Card holders can access chiropractic for specific accepted conditions listed on their card.

WorkCover NSW. Chiropractic treatment for a workplace injury is covered through the icare workers compensation scheme in NSW. The treating GP or specialist must certify the injury and the treatment plan. The clinic invoices icare directly. There is no out-of-pocket cost to the patient for approved treatment.

CTP insurance. If a musculoskeletal injury results from a motor vehicle accident in NSW, chiropractic treatment may be covered under the Compulsory Third Party insurance scheme administered by SIRA. The treating practitioner must document the connection between the accident and the injury.

Eligibility: A Quick Reference Guide

Criteria Eligible Not Eligible
Condition duration Chronic: present for 6+ months Acute: recent injury, short-term
Who prepares the plan GP or prescribed medical practitioner Any other provider
Referral required Yes, GP must issue a referral letter Without referral: no rebate
Sessions per year Up to 5 (shared across all allied health) Beyond 5: full private fee applies
MyMedicare registration Plan accessed via registered practice Non-registered: usual GP clinic
Provider type Must be a registered Medicare provider Unregistered providers: no rebate
Condition examples Chronic back pain, osteoarthritis, chronic neck pain Acute sprain, recent injury under 6 months

Options Without a Chronic Condition

Patients without a qualifying chronic condition can still access chiropractic care as a private service. There is no Medicare rebate in this pathway, but private health extras cover applies for policyholders. For new patients at Sydney CBD clinics, a new patient offer is typically available to reduce the cost of the initial consultation and assessment. This is worth confirming with the clinic before booking.

Patients who develop a chronic condition over time, or whose acute condition becomes chronic, can revisit their GP to discuss whether a GPCCMP has become appropriate. The threshold is six months duration or expected duration.

How to Maximise Cover Each Year

For patients using both Medicare and private health insurance, there is a straightforward approach to maximise value across the year. Use the five GPCCMP sessions first. Once those are exhausted, switch to claiming through private health extras for any additional sessions. This preserves the extras limit for the portion of the year beyond the Medicare allocation.

Book the GP appointment in November or December to have the GPCCMP and referral in place before the calendar year turns. Sessions reset on 1 January. Arriving at the new year with a referral already prepared means the first sessions of the year can begin immediately without waiting for a GP appointment.

Review the private health fund’s reset date. If the annual extras limit resets on 1 April, there may be an opportunity to claim both a final session before the reset and an early session after, within the same short window.

When to See a Chiropractor in Sydney

The Medicare eligibility question is often asked by patients who are already in pain and are weighing up whether to proceed with care. Cost is a real consideration. But delayed treatment for chronic musculoskeletal conditions tends to increase the total treatment required, not reduce it. A condition that has been present for six months can typically be addressed within fewer sessions than one that has been present for two years.

Services Australia is the official source for current GPCCMP eligibility requirements, rebate amounts, and provider registration details. Rebate figures are subject to annual MBS indexation, and this page reflects the most current information.

Patients who are unsure whether they qualify for a GPCCMP should raise the question with their GP at the next available appointment. The conversation takes a few minutes and determines whether the Medicare pathway is available before any out-of-pocket costs are incurred.

Conclusion

Medicare can cover chiropractic in Australia, but only through the GPCCMP pathway, only for patients with a qualifying chronic condition, and only for up to five sessions per calendar year. Outside that pathway, private health extras cover and full private fees are the available options. DVA card holders and patients with workplace or CTP injuries have separate funded pathways available.

For Sydney CBD patients managing ongoing back pain, neck pain, or musculoskeletal conditions, the GPCCMP pathway meaningfully reduces the annual cost of ongoing care. Understanding the full breakdown of chiropractor costs in Sydney alongside the available rebates helps patients plan treatment without unexpected bills. Spine and Posture Care accepts patients under the GPCCMP at both its Macquarie Street and Barangaroo locations and can process Medicare and private health claims in clinic.

For questions about costs, payment pathways, or how to arrange a GPCCMP referral before booking, call Spine and Posture Care on (02) 8040 9922 or contact the clinic directly.

For questions about costs, payment pathways, or how to arrange a GPCCMP referral before booking, call Spine and Posture Care on (02) 8040 9922 or contact the clinic directly.

Disclaimer: This article provides general information about Medicare and chiropractic in Australia as of 2026. Medicare rebate amounts and eligibility rules change regularly. Always confirm current details with Services Australia, your GP, or your health fund before making decisions about your care.

Frequently Asked Questions

Does Medicare cover chiropractic in Australia in 2026?

Medicare does not cover standard chiropractic visits in Australia. However, patients with a qualifying chronic musculoskeletal condition can access up to five subsidised chiropractic sessions per calendar year through a GP Chronic Condition Management Plan (GPCCMP). The GP prepares the plan and issues a referral. The Medicare rebate for each session is approximately $56 to $62 as of 2026, though this is subject to annual MBS indexation. Patients should confirm the current rebate amount with their clinic or Services Australia. Outside the GPCCMP pathway, private health extras cover or full private fees apply.

What is the GPCCMP and how is it different from the old CDM or EPC plan?

The GP Chronic Condition Management Plan (GPCCMP) replaced the old GP Management Plan, Team Care Arrangement, and Enhanced Primary Care plan structures on 1 July 2025. The core patient entitlement is unchanged: up to five allied health sessions per calendar year with a Medicare rebate. The main administrative change is that the old requirement to consult with multiple collaborating providers has been removed. GPs now refer patients directly to allied health services without needing a multidisciplinary team structure. Patients who had an older GPMP or TCA in place before 1 July 2025 can continue using those plans until 30 June 2027.

How many chiropractic sessions does Medicare cover per year?

Under the GPCCMP, Medicare covers up to five individual allied health sessions per calendar year. These five sessions are shared across all allied health services on the plan. A patient who sees a chiropractor for three sessions and a physiotherapist for two sessions has used all five for the year. Sessions reset on 1 January each calendar year and do not roll over. Patients of Aboriginal or Torres Strait Islander descent are entitled to ten sessions per year rather than five.

Can I use private health insurance and Medicare for chiropractic at the same time?

A patient cannot claim both Medicare and private health insurance for the same visit. Double-dipping is not permitted. However, both can be used across different visits within the same year. The practical approach is to use the five GPCCMP sessions first and claim the Medicare rebate for those visits. Once those are used, switch to private health extras for any sessions beyond the Medicare allocation. This maximises the value of both entitlements across the calendar year.

Do I need a referral to see a chiropractor in Sydney?

No referral is required to see a chiropractor in Sydney for private chiropractic care. Any patient can book directly and pay the full consultation fee, with private health extras cover applying if the patient holds an eligible policy. A GP referral is only required when accessing the Medicare rebate under the GPCCMP pathway. Without the GPCCMP referral, Medicare does not contribute to the cost of the visit.


The post Does Medicare Cover Chiropractic in Australia? A 2026 Guide for Sydney Patients appeared first on Spine and Posture Care.


from Spine and Posture Care https://ift.tt/Cs1bO67
via IFTTT

Morning Back Pain: Why You Wake Up Stiff and What to Do About It

Waking up stiff is common. Waking up in genuine pain every single morning is not something to push through. The difference between the two matters, and most online guides do not explain it. At Spine and Posture Care, morning back pain is one of the most consistent complaints at first appointments from patients seeking lower back pain treatment in Sydney. 

The reason it keeps returning has far more to do with spinal mechanics than sleep position alone. This guide covers the three types of morning back pain, the biology behind morning stiffness, and the most effective way to manage it from the first alarm.

Why the Back Is Stiffer in the Morning Than Any Other Time of Day

Morning stiffness is not random. Three separate biological processes cause it. They all happen simultaneously during sleep.

The first is disc rehydration. Spinal discs lose fluid throughout the day under the compression of body weight and activity. During sleep, without axial load, the discs rehydrate through a process called imbibition. They absorb water and become slightly more turgid by morning. A more hydrated disc is larger and more pressure-sensitive. For people with a bulging disc or disc degeneration, this overnight swelling explains why the first 30 minutes after rising are the most painful part of the day.

The second process is inflammatory rhythm. The body’s natural anti-inflammatory hormones, primarily cortisol, reach their lowest levels between 2am and 4am. Inflammatory chemicals peak during this same window. For anyone with joint inflammation in the lumbar spine, the inflammatory load on spinal joints is at its highest point exactly when waking.

The third is joint fluid redistribution. Synovial fluid within the lumbar facet joints thickens during prolonged static positioning. The joints become less mobile and more resistant to movement until the fluid redistributes with warmth and activity. This explains why that first walk to the kitchen feels significantly better than the initial stand from bed.

The 3 Types of Morning Back Pain and What Each One Means

Not all morning back pain is the same problem. Identifying which type is present is the most important step. Each type has a different cause, a different clinical significance, and a different response to treatment. At Spine and Posture Care, the warm-up time, pain pattern, and location are used as the primary diagnostic starting points alongside a back pain chiropractor in Sydney assessment of the lumbar joints.

Type 1: Mechanical Morning Stiffness

Mechanical stiffness eases within 10 to 15 minutes of gentle movement. It is the most common type and the least clinically significant in isolation. The cause is static overnight positioning, joint fluid redistribution, and mild muscular tension. Once the person is moving, the joints warm up and the stiffness resolves.

The key feature is how quickly it resolves. If the back feels largely normal within 15 minutes of getting up, the problem is mechanical. It still warrants attention if it is persistent. Repeated mechanical loading without recovery leads to progressive joint restriction over time. But it is not an urgent clinical concern on its own.

Type 2: Inflammatory Morning Pain

Inflammatory morning pain takes 30 to 60 minutes or longer to ease after getting up. It is often a deeper, more bilateral ache rather than localised stiffness. This extended warm-up time separates inflammatory from mechanical morning pain. It reflects active joint inflammation rather than simple mechanical restriction.

Conditions that cause this pattern include ankylosing spondylitis, reactive arthritis, and inflammatory disc disease. These require investigation beyond mechanical treatment alone. If morning stiffness consistently takes more than 30 minutes to ease, and is accompanied by fatigue or discomfort at other joints, a clinical assessment is the appropriate step. Screening for inflammatory markers is part of the initial assessment when this pattern is present.

Type 3: Disc-Related Morning Pain

Disc-related morning pain is worst in the first 20 to 30 minutes after rising from a lying position. The cause is specific to the disc. After overnight rehydration, the disc is at its most turgid. The transition from lying to standing compresses the swollen disc against sensitised neural tissue. Pain peaks at or shortly after standing. It typically improves after 20 to 30 minutes but returns with prolonged sitting during the day.

This type indicates active disc irritation. People with this pattern describe it as the worst pain of the day, with afternoons being more manageable. Generic stretching advice designed for mechanical stiffness does not address the disc component. It can aggravate the disc if the wrong movements are used.

Why Lower Back Pain Becomes More Common During Perimenopause

The Most Common Causes of Morning Lower Back Pain

Understanding the type of morning pain is step one. Understanding the underlying cause is step two. The most common causes in patients presenting with morning lower back pain at both Sydney CBD locations are listed below.

Sustained daytime loading. The lumbar spine accumulates compressive and shear load throughout the day. When this exceeds the spine’s overnight recovery capacity, the morning pain threshold is lower. A full day at a desk followed by an evening on the couch provides minimal movement variation. The spine arrives at bedtime already fatigued.

Sleep position. Stomach sleeping maintains lumbar hyperextension for six to eight hours. Side sleeping without pillow support between the knees creates sustained pelvic rotation. Both positions accumulate rather than offload the load patterns built up during the day.

Mattress failure. A mattress that has lost its support allows the pelvis to sink below the shoulders and feet. This creates a sustained flexion or extension position and replicates the same loading problems that caused the daytime pain.

Lumbar facet joint restriction. Facet joints that have lost normal movement range become progressively stiffer during the inactivity of sleep. They require mobilisation to restore normal glide. Morning movement alone does not fully correct a structural restriction.

Disc degeneration or bulge. Both conditions change how the disc responds to the overnight rehydration cycle. A degenerated disc has reduced fluid absorption capacity. A bulging disc may press more directly on neural tissue when at its most hydrated in the morning.

Deconditioned spinal stabilisers. Weak deep stabilising muscles allow the spine to shift into unsupported positions during sleep. The multifidus and transversus abdominis are the primary structures involved. When these are not functioning adequately, joint compression increases in whatever position the body holds for hours at a time.

If morning back pain has been a daily pattern for more than two weeks, the spine is asking for a clinical review. Call (02) 8040 9922 or get in touch here to book an assessment at our Sydney CBD clinic.

What to Do in the First 10 Minutes After Waking

The first 10 minutes after waking makes a measurable difference to how the rest of the day feels. At Spine and Posture Care, this protocol is recommended for patients managing both mechanical and disc-related morning back pain. The goal is to progressively offload and then reload the lumbar spine rather than moving straight from lying to standing under full compression.

Before getting up (60 seconds). Stay lying on the back. Draw both knees toward the chest and hold for 30 seconds. This gently decompresses the lumbar facet joints and releases the posterior hip capsule before any weight-bearing load is added.

Pelvic tilts (2 minutes). Still lying flat, gently flatten the lower back into the mattress and release. Ten slow repetitions. This activates the deep stabilising muscles, begins circulating synovial fluid, and prepares the lumbar spine for the transition to standing.

Rising from bed carefully. Roll to one side before pushing up to seated. Avoid sitting straight up from flat. This position places significant flexion load on the anterior discs at the exact time they are most sensitised from overnight rehydration.

Heat application (5 to 10 minutes). A heat pack on the lumbar region for the first 10 minutes increases blood flow to the paraspinal muscles. It reduces joint capsule tension and makes the lumbar spine more receptive to movement. A warm shower achieves the same result. Heat is appropriate for chronic morning stiffness. Cold is appropriate for acute injuries.

Gentle standing extension (10 minutes in). Once upright and warmed, place hands on the lower back and gently extend backwards five times. This decompresses the anterior disc and helps restore the natural lumbar curve after the overnight resting position.

Green Flags and Red Flags: How to Read the Signs

Sign Green Flag Red Flag
Warm-up time Eases within 15 minutes Takes longer than 30 to 60 minutes
Pattern over time Stays about the same Getting progressively worse
Location Central lower back One-sided or radiating into the leg
Night pain Pain only on waking Wakes from sleep during the night
Associated symptoms None Bladder or bowel changes, fever, weight loss
Duration Less than 6 weeks More than 6 weeks
Response to movement Clearly improves Worsens or stays the same

Green flag presentations are suitable for self-management alongside a clinical review if they persist. Red flag presentations require professional evaluation before self-management, as they may indicate conditions that need investigation beyond mechanical treatment.

When to See a Chiropractor for Morning Back Pain in Sydney

Morning back pain that matches any red flag above warrants prompt clinical assessment. Persistent mechanical stiffness present for more than two weeks without improvement also warrants review. The structural restriction underlying most cases tends to worsen without treatment rather than resolve on its own.

Healthdirect Australia, the national government health information service, recommends professional assessment when back pain is not improving after a few weeks. It also applies when any red flag sign is present. A chiropractor assesses the mobility of each lumbar vertebral level, identifies restricted facet joints and disc involvement, and evaluates deep stabilising muscle function. From that assessment, a targeted treatment plan addresses the specific structural cause.

The most important reason to seek assessment early is that the three types of morning back pain respond to different approaches. Managing Type 3 disc-related pain with the stretches used for Type 1 mechanical stiffness can aggravate the disc. A clinical diagnosis determines the correct approach before treatment begins.

Conclusion

Morning back pain has a specific biological explanation. Disc rehydration, inflammatory rhythm, and joint fluid redistribution all combine to make the lumbar spine maximally sensitised at the moment of waking. Understanding which of the three types is present determines both the urgency of clinical assessment and the most effective self-management approach.

The morning protocol in this guide reduces the load placed on the lumbar spine in the transition from sleeping to standing. Combining it with addressing the best sleeping positions for lower back pain directly targets the overnight loading patterns that set the morning pain threshold.

 For people whose stiffness exceeds 30 minutes, is worsening, or is accompanied by any red flag sign, Spine and Posture Care provides a full lumbar assessment at the first appointment to identify the structural cause.

If morning back pain is affecting the start of every day, call Spine and Posture Care on (02) 8040 9922 or contact the clinic directly to arrange an assessment. Appointments are available throughout the week at both Macquarie Street and Barangaroo CBD locations.

Frequently Asked Questions

Why is lower back pain always worse in the morning?

Lower back pain is typically worse in the morning because of three overlapping biological processes during sleep. First, spinal discs rehydrate overnight and become more pressure-sensitive by morning. Second, the body’s natural anti-inflammatory hormones are at their lowest between 2am and 4am, while inflammatory chemicals peak during this window. Third, synovial fluid in the lumbar facet joints thickens during prolonged inactivity and resists movement until redistributed with warmth and load. All three processes resolve with movement and the body’s normal hormonal wake cycle, which is why morning back pain typically improves as the day progresses.

How long should morning back stiffness last before seeing a chiropractor?

Morning back stiffness that eases within 10 to 15 minutes of gentle movement is typical mechanical stiffness. It can initially be managed with a morning movement routine and sleep position correction. Stiffness that takes more than 30 to 60 minutes to ease, or that has been present daily for more than two weeks without improvement, warrants clinical assessment. Stiffness accompanied by pain radiating into the leg, bladder or bowel changes, fever, or pain that wakes from sleep requires prompt professional evaluation to rule out inflammatory or serious spinal conditions.

Is morning back stiffness a sign of arthritis?

Morning back stiffness can be associated with arthritis, but most cases in adults under 60 have a mechanical rather than arthritic cause. Osteoarthritis of the lumbar facet joints does produce morning stiffness, typically easing within 15 to 30 minutes of movement. Inflammatory arthritis conditions such as ankylosing spondylitis produce a different pattern: stiffness lasting more than 30 to 60 minutes, often affecting the sacroiliac joints and lower lumbar spine bilaterally, and typically presenting in adults under 45. If morning stiffness is taking a long time to ease and is progressively worsening, an assessment that includes inflammatory screening is the appropriate step.

What stretches help morning lower back pain?

The most effective movements in the first few minutes after waking are those that gently decompress the lumbar joints. Knee-to-chest holds with both knees together (30 seconds), pelvic tilts lying flat (10 gentle repetitions), and cat-cow movements on all fours are appropriate for most people with mechanical morning stiffness. Standing lumbar extensions with hands on the lower back (five gentle repetitions) are useful once upright. Flexion-based stretches such as seated forward bends should be avoided in the first 30 minutes for people with disc-related pain. The disc is at its most turgid and pressure-sensitive at this time, and forward bending increases disc compression.

Can a Sydney CBD chiropractor help with chronic morning back pain?

Yes. Chronic morning back pain that has been present for months without resolution is well suited to chiropractic assessment because the underlying structural cause has rarely been directly addressed. A chiropractor assesses the mobility of each lumbar vertebral level, evaluates the discs and surrounding soft tissue, and tests the deep stabilising muscles. Treatment addresses the structural causes through joint mobilisation, disc-specific rehabilitation if indicated, and progressive core stabilisation. Most patients with chronic mechanical morning stiffness notice significant improvement within four to eight sessions when treatment is combined with sleep position correction and the morning protocol described in this article.

The post Morning Back Pain: Why You Wake Up Stiff and What to Do About It appeared first on Spine and Posture Care.


from Spine and Posture Care https://ift.tt/fvI8mYQ
via IFTTT

Mid Back Pain Between the Shoulder Blades: 6 Causes Sydney Desk Workers Face

That dull ache between the shoulder blades at 3pm on a Tuesday is not random. For the thousands of people working at desks in Macquarie Street towers, Barangaroo offices, and CBD co-working spaces, mid back pain treatment in Sydney is one of the most requested services at Spine and Posture Care. 

There are six specific causes behind it. Most desk workers are dealing with all six at once. This article breaks each one down.

What Is Actually Happening Between the Shoulder Blades

The area between the shoulder blades corresponds to the mid-thoracic spine, roughly T4 to T8. This region sits between two highly mobile zones: the cervical spine above and the lumbar spine below. The thoracic spine is built for stability. It tolerates sustained load poorly.

Three main structures generate pain here. The thoracic facet joints become compressed under sustained forward bending. The rhomboids and mid-trapezius muscles are placed under prolonged load when the shoulders round forward. The interscapular ligaments are overstretched when the thoracic spine stays flexed for hours. Poor posture treatment addresses all three structures because the underlying postural mechanics drive each one.

Understanding which structure is generating the pain matters. A thoracic facet irritation feels different from a rhomboid strain. The treatment approach differs accordingly. Most generic advice treats all mid back pain as a muscle problem, which misses the joint and ligament contributions entirely.

Causes 1 to 3: Structural Load Problems

These three causes relate to how the spine and surrounding muscles are mechanically loaded during desk work. A chiropractor in Sydney CBD can assess which of these is contributing most to a specific presentation. In practice, all three commonly occur together. At Spine and Posture Care, this combination is the most consistent finding in patients presenting with interscapular pain from desk work.

Cause 1: Sustained Thoracic Flexion

The single biggest driver of mid back pain in desk workers is sitting in thoracic flexion for hours without a break. When the thoracic spine rounds forward, the posterior facet joints are compressed. The anterior discs are loaded asymmetrically. The posterior ligaments are placed under continuous stretch.

The problem is not any single moment of poor posture. It is the total duration. Thoracic flexion that lasts more than 30 minutes without interruption consistently produces facet joint irritation in office patients. Sydney open-plan offices discourage the movement breaks that would prevent this loading from becoming painful. The body was built to shift between postures throughout the day. Desk culture removes that option.

Cause 2: Thoracic Facet Joint Dysfunction

Thoracic facet joints are small, cartilage-lined joints located on both sides of each vertebral level. Under sustained flexion, the joint surfaces are pressed together. The joint capsules become chronically inflamed. When this is not addressed, the joints lose their normal glide and become restricted.

Restricted thoracic facets produce a deep, localised ache between the shoulder blades. It worsens when sitting still and eases briefly with movement. That response to movement is the key clinical feature. It separates facet joint dysfunction from pure muscle pain, which typically worsens with movement rather than improving. Facet joint dysfunction requires direct joint mobilisation. Stretching and massage alone do not restore the movement restriction.

Cause 3: Rhomboid and Mid-Trapezius Overload

The rhomboids and mid-trapezius are responsible for retracting the shoulder blades. In a rounded-shoulder desk posture, they work against the constant forward pull of the arms and the pectoral muscles. Electromyography research shows these muscles fire at roughly three times their normal rate when the head sits 5 centimetres in front of the torso.

Over a full working day, this sustained overactivation produces fatigue and myofascial trigger points within the muscle belly. These trigger points create the dull, burning referral pattern that desk workers describe as tension between the shoulder blades. The muscles need to shorten and recover. That recovery can only happen when the underlying postural load is removed.

chiropractor consulting patient about mid back pain treatment in Sydney

Causes 4 to 6: Workplace and Lifestyle Triggers

These three causes sit at the intersection of workspace setup and daily habits. They amplify the structural problems above. They are also the reason the same desk posture affects some workers more severely than others.

Cause 4: Monitor Height and Screen Distance

A monitor positioned too low forces the head to tilt down. This adds cervical flexion load directly to the upper thoracic spine. A 5-kilogram head becomes a 15-kilogram load when tilted 30 degrees forward. That load concentrates at T4 to T6.

Screen distance is equally problematic. A monitor placed too far from the seated worker causes a compensatory forward lean of the trunk. This compounds the thoracic flexion load from Cause 1. The correct setup positions the top of the screen at eye level, at arm’s length from the seated position. Most Sydney CBD workstations, particularly hot-desks and meeting-room setups, do not meet this standard.

Cause 5: Scapular Dyskinesis from Asymmetric Desk Habits

Scapular dyskinesis refers to abnormal movement and positioning of the shoulder blade. In desk workers, it develops from asymmetric habits. Using a mouse on one side, holding a phone between the ear and shoulder, or rotating to a second screen all create loading imbalances over time.

These patterns alter the resting position of the scapula. The serratus anterior on the loaded side becomes inhibited. The upper trapezius on the same side becomes overactive. The rhomboids on the opposite side are placed under constant stretch. The result is pain that is worse on one side of the interscapular region. Most Sydney desk workers with this cause describe their pain as predominantly right-sided, corresponding to the dominant mouse hand.

Cause 6: Stress-Driven Muscle Guarding

The mid-back is a primary site where the body holds physical tension in response to psychological stress. When the sympathetic nervous system is activated by workplace pressure, the paraspinal and interscapular muscles contract reflexively. In a demanding CBD work environment, this activation becomes near-continuous.

The problem is that this response is subconscious. Most workers do not notice the guarding until it crosses the pain threshold. By that point, the muscles have been contracted for hours. This cause is particularly relevant in Sydney CBD environments where deadline pressure, open-plan noise, and extended screen time maintain sympathetic nervous system activation throughout the day.

Mid back pain that appears every afternoon is telling you something structural needs attention. Call (02) 8040 9922 or get in touch here
to book an assessment at our Sydney CBD clinic.

Why These 6 Causes Stack Against Each Other

None of these six causes operates alone. Sustained thoracic flexion leads to facet joint dysfunction. Facet dysfunction reduces the spine’s ability to self-correct, which increases rhomboid and trapezius overload. A poorly positioned monitor drives the head forward and amplifies both the flexion load and muscle overload. Asymmetric habits create imbalances that make the spine more vulnerable to all of the above. Stress keeps the muscles contracted so they cannot recover during quieter periods.

The clinical result is a spine that is simultaneously stiff, inflamed, overloaded, and unable to recover between working days. At Spine and Posture Care, this pattern is one of the most consistent findings in CBD patients: pain worsens across the working week, eases slightly on weekends, and returns by Tuesday or Wednesday. The weekend provides partial recovery. The working week rebuilds all six causes before that recovery is complete.

Breaking this cycle requires addressing the structural drivers. Heat packs and over-the-counter pain relief manage the pain threshold. They do not restore facet joint movement, reduce rhomboid trigger points, or correct scapular positioning.

What Sydney CBD Desk Workers Can Do Right Now

Practical changes reduce the daily load while the underlying problem is being treated. These steps do not replace clinical assessment, but they reduce the accumulation of all six causes.

Set a movement timer for every 30 minutes. Standing up, walking to a colleague, or taking a call while walking all break the sustained thoracic flexion cycle. Two minutes of movement every 30 minutes is more protective than a 20-minute walk at lunch.

Raise the monitor. A monitor riser or a stack of books under a laptop stand removes the head-down flexion load from the upper thoracic spine. The top of the screen should align with eye level when seated upright. This single change directly addresses Cause 1, Cause 2, and Cause 4 simultaneously.

Use a lumbar support. Supporting the lower back maintains the lumbar curve. This reduces the compensatory thoracic rounding that loads the interscapular region. The thoracic and lumbar curves are mechanically linked. Supporting one assists the other.

All 6 Causes at a Glance

Cause Structure Affected Key Driver Typical Pattern
Sustained thoracic flexion Facet joints, posterior ligaments Sitting without breaks Central ache, worsens through the day
Thoracic facet joint dysfunction Facet joints T4 to T8 Cumulative flexion load Deep ache, eases briefly with movement
Rhomboid and trapezius overload Interscapular muscles Forward head, rounded shoulders Burning tension between shoulder blades
Monitor height and distance Cervical and upper thoracic spine Screen too low or too far Pain worse at screen, eases off screen
Scapular dyskinesis Serratus anterior, rhomboids, upper trapezius Asymmetric mouse and phone use One-sided pain, worse on dominant side
Stress-driven muscle guarding Paraspinal and interscapular muscles Sustained sympathetic activation Peaks in afternoon, eases on weekends

When to See a Chiropractor for Mid Back Pain in Sydney

Mid back pain that has been present for more than two weeks, is interfering with work concentration, is not responding to postural changes, or is accompanied by arm or ribcage pain warrants a clinical assessment. SafeWork NSW recognises computer workstation-related musculoskeletal conditions as a significant category of workplace injury. Persistent interscapular pain falls within this category.

A chiropractor assesses the thoracic facet joints through motion palpation, identifies overloaded muscle groups through orthopaedic testing, and evaluates scapular positioning and movement. From that assessment, a treatment plan addresses the structural causes through joint mobilisation, soft tissue work, and postural rehabilitation. Scapular stabiliser rehabilitation is a critical component. Without it, the muscle imbalances that allow all six causes to develop remain in place after the acute pain settles.

Waiting for the pain to resolve over a long weekend is a common response. For mild, acute presentations it sometimes works. For the layered pattern described in this article, where multiple causes have been accumulating for months, it consistently does not.

Conclusion

Mid back pain between the shoulder blades in Sydney desk workers is the predictable result of six causes operating simultaneously: sustained thoracic flexion, facet joint dysfunction, rhomboid and trapezius overload, poor monitor setup, scapular dyskinesis, and stress-driven muscle guarding. Addressing one while leaving the others in place produces partial, temporary relief.

For desk workers whose working from home back pain or in-office pain has become a daily pattern, a structural assessment identifies which causes are most active and builds a targeted treatment plan. Spine and Posture Care provides a full thoracic and postural assessment at the first appointment, including a specific review of the workplace factors contributing to the presentation.

If mid back pain between the shoulder blades is affecting work performance or daily life, call Spine and Posture Care on (02) 8040 9922 or contact the clinic directly to arrange an assessment. Appointments are available throughout the week at both the Macquarie Street and Barangaroo CBD locations.

Frequently Asked Questions

What causes mid back pain between the shoulder blades in desk workers?

Mid back pain between the shoulder blades in desk workers typically results from a combination of six factors. Sustained thoracic flexion compresses the facet joints of the mid-spine. The rhomboid and mid-trapezius muscles become overloaded from holding the shoulder blades against the pull of rounded shoulders. A monitor positioned too low adds cervical and thoracic flexion load. Asymmetric habits such as one-sided mouse use create scapular imbalances that produce one-sided interscapular pain. Workplace stress drives subconscious muscle guarding that keeps the interscapular muscles contracted throughout the day. Most desk workers present with all of these factors active simultaneously, which is why the pain becomes persistent rather than resolving on its own.

Is mid back pain between the shoulder blades serious?

In most desk workers, mid back pain between the shoulder blades is a mechanical musculoskeletal problem rather than a sign of a serious condition. The pain comes from the joints, muscles, and ligaments of the thoracic spine responding to sustained load. However, mid back pain accompanied by shortness of breath, chest pain, or pain radiating into the jaw warrants urgent medical assessment to rule out cardiac causes. Mid back pain that is progressively worsening without a clear desk-work trigger also warrants investigation. For the typical desk worker presentation, a chiropractic assessment is the appropriate first step.

How long does mid back pain between the shoulder blades take to resolve with chiropractic treatment?

Most desk workers notice significant improvement within three to six chiropractic sessions when structural causes are addressed alongside workstation corrections. Cases where facet joint dysfunction has been present for months, or where significant muscle trigger points have developed, require a longer rehabilitation phase to restore full scapular stability and prevent recurrence. Recovery speed is strongly influenced by whether workplace ergonomics are also corrected during the treatment period. Pain that returns to the same level between sessions usually means the daily loading pattern has not changed.

Can a chiropractor in Sydney CBD help with mid back pain between the shoulder blades?

Yes. Chiropractic assessment is well suited to desk-related mid back pain. A chiropractor assesses the mobility of each thoracic vertebral level, identifies restricted facet joints through motion palpation, and evaluates scapular positioning and muscle recruitment patterns. Treatment includes joint mobilisation, soft tissue therapy, and postural rehabilitation. The rehabilitation component, which focuses on reactivating the mid and lower trapezius and serratus anterior, is what prevents the pain from returning once the acute symptoms settle. Without this phase, the muscle imbalances that caused the problem remain in place.

What is the fastest way to relieve mid back pain between the shoulder blades at a desk?

The fastest immediate relief comes from standing and gently extending the thoracic spine in the opposite direction to the seated flexion position. Standing, placing the hands on the lower back, and gently extending backwards for 10 seconds decompresses the posterior facet joints and gives overstretched posterior ligaments brief relief. Setting a timer to repeat this every 30 minutes throughout the working day significantly reduces the total compression load. This is not a treatment for the underlying causes, but it interrupts the cycle of sustained compression. For resolution of the structural causes, a clinical assessment and targeted treatment plan is necessary.

The post Mid Back Pain Between the Shoulder Blades: 6 Causes Sydney Desk Workers Face appeared first on Spine and Posture Care.


from Spine and Posture Care https://ift.tt/Jfnupki
via IFTTT

The Best Sleeping Position for Lower Back Pain (and the 3 to Avoid)

Lower back pain does not stop when the lights go out. For many people seeking lower back pain treatment in Sydney, nights are just as difficult as days. 

At Spine and Posture Care, the same question comes up constantly in initial consultations: does sleep position actually matter? The answer is yes, and the wrong position can undo the recovery the body would otherwise make overnight. 

This guide covers the positions that help, the three that hurt, and what to do when position changes alone are not enough.

Why Sleep Position Has a Direct Impact on Lower Back Pain

The lumbar spine carries most of the body’s load throughout the day. During sleep, the goal is to offload that pressure completely. This allows the discs, joints, and supporting muscles to recover. A neutral spine position achieves this. A poor sleep position does the opposite.

Poor sleep alignment keeps the lumbar region under load, increases compression on spinal joints, and inflames already irritated tissues overnight. Research confirms that posture during rest is one of the key modifiable factors in managing back pain.

Sleep position also interacts with the underlying cause of the pain. A position that suits someone with general muscular tightness may aggravate someone with a bulging disc or spinal stenosis. Understanding which positions help which conditions is the missing piece most online guides skip.

The Best Sleeping Positions for Lower Back Pain

There is no single position that suits every person or every condition. But three positions consistently reduce lumbar load and support spinal alignment across the most common presentations. At Spine and Posture Care, these are the starting points for sleep position advice at every initial consultation.

Side Sleeping with a Pillow Between the Knees

This is the most widely recommended position for lower back pain. Lying on one side with a slight bend at the hips and knees puts the lumbar spine in a near-neutral position. Without a pillow between the knees, the top leg drops forward. That forward drop rotates the pelvis and creates a twisting force through the lower back.

Placing a firm pillow between the knees keeps the hips, pelvis, and lumbar spine stacked in alignment. A rolled towel at the waist fills the gap between the ribcage and hip if the mattress does not provide support in that zone. Switch sides from night to night. Consistently favouring one side can create muscular imbalances over time.

Back Sleeping with a Pillow Under the Knees

Back sleeping distributes body weight more evenly than any other position. The spine rests flat, pressure is shared across a larger surface area, and there is no rotational load through the lumbar joints. Lying completely flat tends to flatten the natural lumbar curve, which creates a low-grade pull on the lower back muscles and ligaments.

Placing a pillow under the knees solves this. Slightly elevated knees restore the lumbar curve to a neutral position, reduce tension in the hip flexors, and take pressure off the lower discs. This position is particularly effective for people with generalised lower back stiffness or facet joint irritation.

The Foetal Position

For people with spinal stenosis, the foetal position offers specific relief. Drawing the knees toward the chest gently opens the spaces between the vertebrae. This reduces pressure on the nerves passing through those gaps. The foetal position is not ideal for disc-related pain, as it increases flexion load on the anterior disc. For stenosis, however, it is often the only position that allows sleep without pain.

The 3 Sleeping Positions to Avoid

Most guides list one bad position. There are three, each harmful in a different way. Understanding the mechanism helps explain why the pain keeps returning despite other changes.

1. Flat Stomach Sleeping

Sleeping face-down is the most damaging position for the lower back. When lying prone, the middle of the body sinks into the mattress under gravity. This forces the lumbar spine into hyperextension. The posterior joints are compressed, the rear portion of the intervertebral discs is squeezed, and load is placed on the exact structures most commonly irritated in lower back pain.

The problem compounds because the head must rotate to one side to breathe. That rotation creates a cervical twist that travels through the thoracic and lumbar spine. This pattern of sustained night-time compression directly contributes to lower back pain symptoms that are consistently worse first thing in the morning.

2. Stomach Sleeping with a Pillow Under the Abdomen Only

Some guides recommend placing a pillow under the pelvis for stomach sleepers. This is a partial fix, not a solution. The pillow reduces the degree of lumbar hyperextension but does not eliminate it. The head rotation problem remains throughout the night.

If stomach sleeping is the only position a person can fall asleep in, a thin pillow under the lower abdomen is better than nothing. It is a harm-reduction measure rather than a genuine solution. The goal should be to gradually transition to side or back sleeping over time.

3. Side Sleeping Without Pillow Support

Side sleeping without a pillow between the knees looks like good sleep hygiene. In practice, it functions like a slow rotational injury over six to eight hours. When the top knee drops toward the mattress, the pelvis rotates forward. The lumbar spine follows that rotation and holds that position through the night.

This sustained torsion loads the facet joints and stretches the piriformis and sacroiliac ligaments on the upper side. It is one of the most common presentations seen by a back pain chiropractor in Sydney and one of the simplest to fix. A firm pillow between the knees resolves the rotational load immediately.

Which Position Works Best for Each Condition

Not all lower back pain is the same. The table below reflects the clinical approach used at Spine and Posture Care when guiding patients on sleep position based on a specific diagnosis.

Condition Recommended Position Avoid
General lower back pain Side sleeping with pillow between knees Flat stomach sleeping
Bulging or herniated disc Side sleeping, knees slightly drawn up Foetal position, stomach sleeping
Spinal stenosis Foetal position or side sleeping Flat back sleeping
Sciatica Side sleeping on the non-affected side Stomach sleeping, unsupported side sleeping
Facet joint irritation Back sleeping with pillow under knees Stomach sleeping, deep foetal position
General stiffness Back sleeping with pillow under knees Stomach sleeping

The position that suits the condition matters more than the position that feels comfortable at the start of the night. Comfort at sleep onset and comfort at 6am are often very different things.

Bulging Disc Causes And Symptoms Among Sydney Residents

Setting Up the Sleep Environment

Position is only part of the equation. A poor mattress or pillow can neutralise even the best sleeping position. People managing persistent lower back pain throughout the day and sleeping on a sagging mattress get no recovery window at all.

A medium-firm mattress provides the best combination of support and pressure relief for lower back pain. Mattresses that are too soft allow the pelvis to sink. This recreates the lumbar hyperextension problem regardless of the sleep position chosen. Mattresses that are too firm create pressure points at the hips and shoulders, which causes the body to shift during the night to relieve that discomfort.

Pillow height matters as much as mattress firmness. For side sleepers, the pillow should fill the gap between the head and shoulder, keeping the cervical spine level. For back sleepers, a thinner pillow is better. A thick pillow pushes the head forward and increases tension through the neck and upper back.

Lower back pain that disrupts sleep needs a clinical assessment, not just a better pillow. Call (02) 8040 9922 or get in touch here to book an appointment with the team at our Sydney CBD clinic.

Why Some People Still Wake Up in Pain After Changing Position

Changing sleep position is a meaningful step, but it does not address structural problems that make the lower back vulnerable in the first place. Joint dysfunction, disc irritation, and muscular imbalances do not resolve from positional changes alone.

Understanding the lower back pain causes behind a specific presentation determines whether sleep position is the main issue or a contributing factor. In many cases, the back is already irritated from daytime loading patterns. Sleep position is then the variable that tips the pain threshold over during the night.

Core stability is also relevant here. A spine with poor deep muscular support is less able to maintain a neutral position throughout the night. The body shifts during sleep. A spine without adequate muscular control will drift into aggravating positions by 3am regardless of how it was arranged at bedtime.

All Sleep Positions Compared at a Glance

Sleep Position Effect on Lower Back Best Suited For Rating
Side sleeping with pillow between knees Maintains pelvic and lumbar alignment Most lower back conditions Best
Back sleeping with pillow under knees Distributes load evenly, restores lumbar curve Facet joint pain, general stiffness Very good
Foetal position Opens vertebral spaces, reduces nerve pressure Spinal stenosis Good for stenosis only
Side sleeping without pillow support Creates sustained lumbar rotation No one Avoid
Stomach sleeping with pelvis pillow Partial reduction of hyperextension None ideally Last resort only
Flat stomach sleeping Hyperextends lumbar spine, rotates cervical spine No one Avoid

When to See a Chiropractor for Lower Back Pain

Sleep position changes are a self-management tool, not a treatment. If lower back pain has persisted for more than two weeks, is waking a person from sleep, is accompanied by pain radiating into the leg, or shows no improvement with positional adjustments, a clinical assessment is the appropriate next step. The Better Health Channel, published by the Victorian Government, identifies these as the key indicators that back pain requires professional evaluation.

A chiropractor assesses the joints, discs, and muscles of the lumbar spine to identify the structures involved. From that assessment, a treatment plan addresses the underlying cause rather than the symptoms. Sleep position guidance forms part of that plan alongside joint mobilisation, soft tissue work, and exercise rehabilitation.

Waiting for back pain to resolve on its own is a common strategy. For disc-related pain, joint dysfunction, or nerve involvement, it tends to allow the condition to progress before treatment begins.

Conclusion

Sleep position is one of the most actionable changes a person with lower back pain can make tonight. Side sleeping with a pillow between the knees, back sleeping with a pillow under the knees, and the fetal position for stenosis-related pain are the three positions consistently supported by clinical evidence. Flat stomach sleeping, stomach sleeping with head rotation, and unsupported side sleeping are the three to remove immediately.

For people whose pain persists despite these adjustments, the issue lies in the underlying spinal mechanics rather than sleep habits alone. The lower back pain causes behind a specific presentation need to be identified and addressed for lasting relief. Spine and Posture Care provides a full spinal assessment at the first appointment, including a sleep and posture review as part of the intake process.

If lower back pain is disrupting sleep and daily life, call Spine and Posture Care on (02) 8040 9922 or contact the clinic directly to arrange an assessment. Appointments are available throughout the week, including early morning and Saturday sessions.

Frequently Asked Questions

What is the best sleeping position for lower back pain?

Side sleeping with a firm pillow between the knees is the most widely recommended position for lower back pain. This position keeps the hips, pelvis, and lumbar spine aligned, which reduces joint compression and prevents the rotational load that comes from the top knee dropping forward. Back sleeping with a pillow under the knees is an equally strong alternative, particularly for people with facet joint irritation or generalised stiffness. The key in both cases is support: without the pillow, neither position fully eliminates the mechanical load on the lower back.

Why does lower back pain feel worse in the morning than it did the night before?

Morning lower back pain that is worse than the evening pain is most commonly caused by one of three things: poor sleep position maintaining lumbar compression overnight, a mattress that allows the spine to sag out of alignment, or an underlying disc or joint issue that responds poorly to prolonged static loading. In many cases it is a combination. The inflammatory chemicals released by irritated spinal tissue peak in the early morning hours, which is why stiffness and pain are often worst for the first 30 to 60 minutes after waking. If this pattern is consistent, a clinical assessment is worthwhile to identify the structural cause.

Is stomach sleeping always bad for lower back pain?

Stomach sleeping is the least recommended position for lower back pain because it places the lumbar spine in sustained hyperextension and forces the head to rotate to one side for hours at a time. This compresses the facet joints, loads the posterior discs, and creates a twisting force from the cervical spine down to the lumbar region. If stomach sleeping is the only way to fall asleep, placing a thin, flat pillow under the lower abdomen reduces the degree of lumbar extension. This is a harm-reduction measure. Over time, conditioning the body to tolerate side sleeping is a better strategy for long-term lower back health.

Does mattress firmness affect lower back pain during sleep?

Yes, mattress firmness has a direct effect on spinal alignment during sleep. A mattress that is too soft allows the heaviest part of the body, typically the hips and pelvis, to sink deeper than the shoulders and feet. This creates a hammock-like shape that pushes the lumbar spine out of its natural curve. A medium-firm mattress provides enough pushback to keep the spine level without creating pressure points at the bony prominences. Research consistently supports medium-firm as the optimal range for lower back pain management, and this applies across both side and back sleeping positions.

When should lower back pain during sleep be assessed by a chiropractor in Sydney CBD?

Lower back pain that consistently disrupts sleep, causes pain radiating into the buttock or leg, is accompanied by numbness or tingling in the feet, or shows no improvement after two weeks of conservative management warrants a clinical assessment. Morning pain that takes longer than 30 minutes to ease is another indicator that the underlying structure needs evaluation. A chiropractor in Sydney CBD can assess the lumbar spine, identify whether the issue involves a disc, joint, or nerve, and provide a targeted treatment and rehabilitation plan. Sleep position guidance is one part of that plan, but structural problems in the spine need direct treatment to resolve.


The post The Best Sleeping Position for Lower Back Pain (and the 3 to Avoid) appeared first on Spine and Posture Care.


from Spine and Posture Care https://ift.tt/rDEgbTi
via IFTTT

What to Expect at Your First Chiropractic Appointment in Sydney

First chiropractic appointments in Sydney generate a consistent set of questions before patients even walk through the door. Will it hurt? W...